HIMS manages inpatients on one record: admission and bed allocation, doctor orders and ward rounds, nursing charts, pharmacy and lab against the admission, a running IP bill with interim statements, TPA pre-authorisation and a discharge summary drawn from the notes.
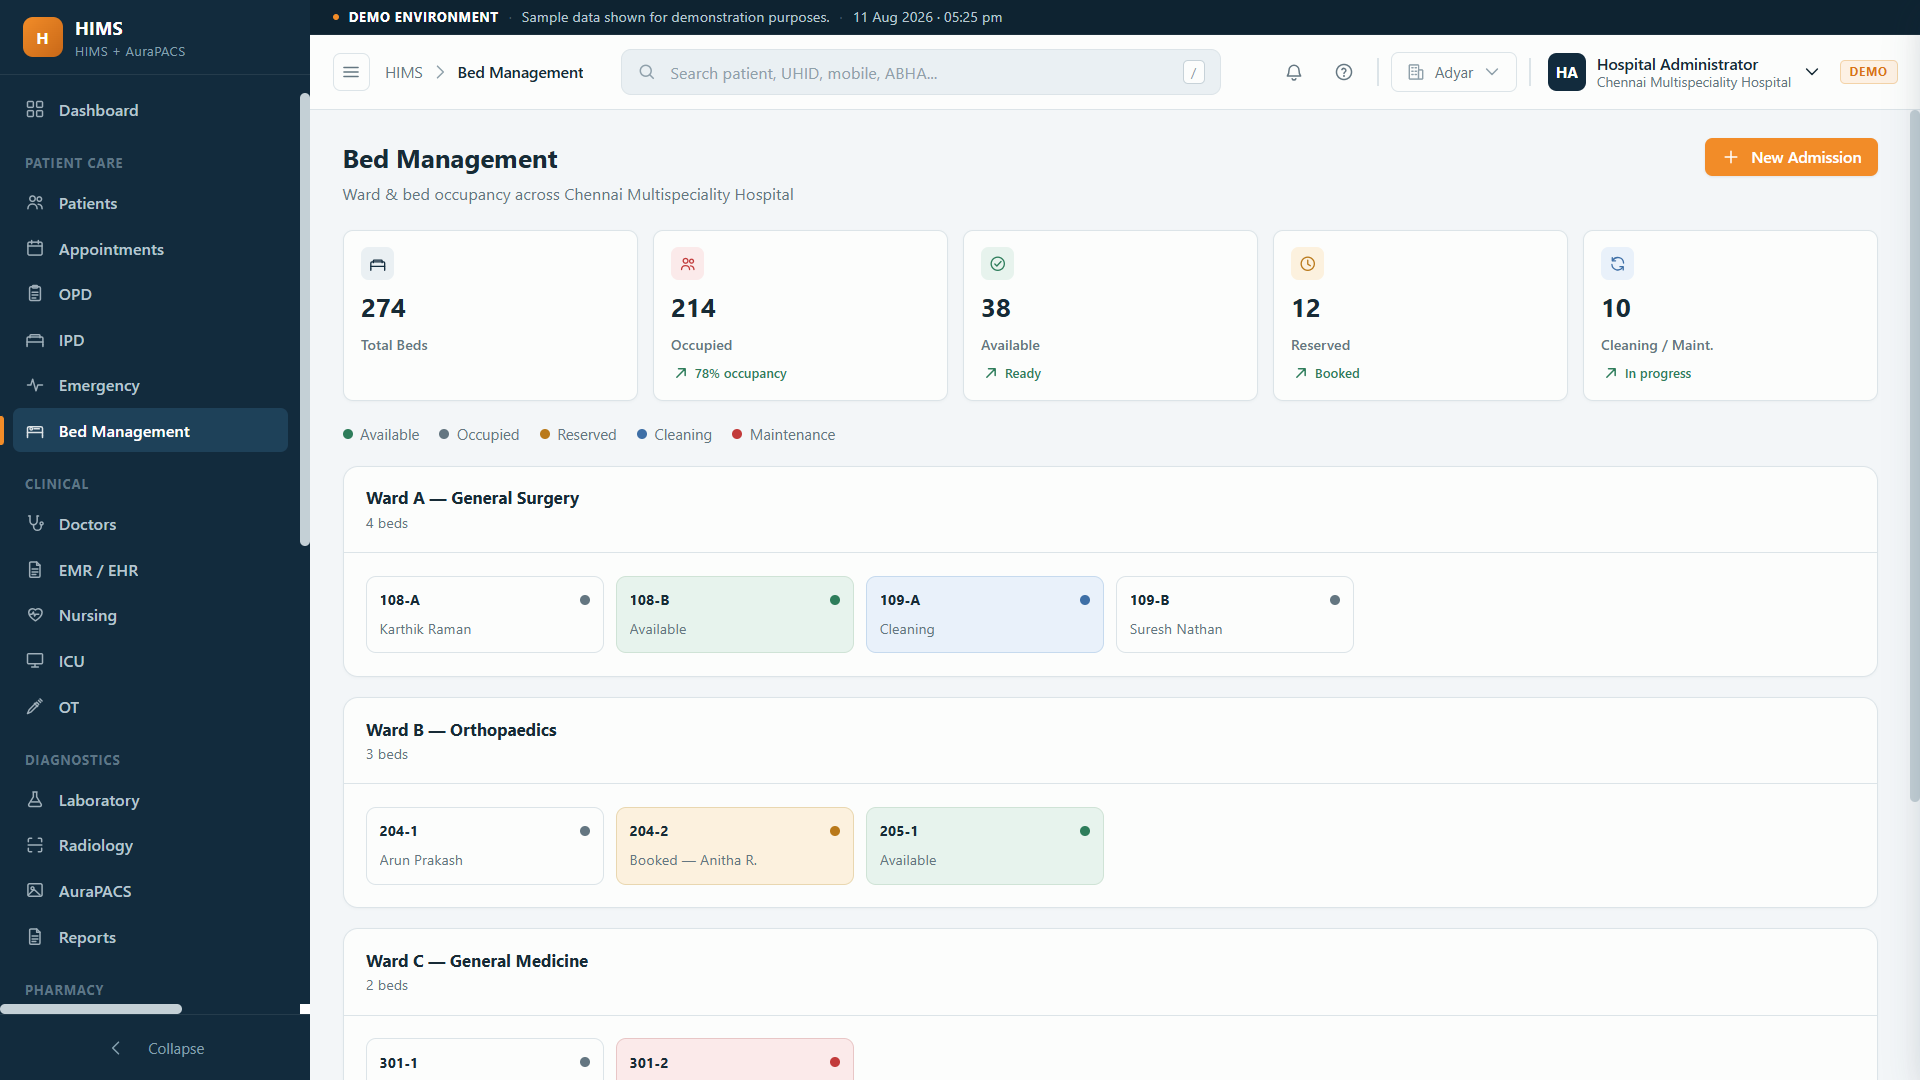
Hospital IPD software handles everything that happens between admission and discharge: allocating a bed, recording doctor orders and ward rounds, keeping nursing charts, issuing drugs and investigations against the admission, running the IP bill as charges accrue, coordinating TPA pre-authorisation and producing the discharge summary. In HIMS the inpatient workflow is a continuation of the same record that OP or casualty created.
The difference from an OP visit is time and money. An admission runs for days, involves several shifts of staff and accumulates charges from pharmacy, lab, OT and the ward. HIMS keeps that running total visible so an interim bill can be printed for the family or the TPA at any point, and the final bill at discharge is what the record says, not what someone reconstructed.
The longer the stay, the more places a charge or an order can fall through.
The ward knows which bed is taken; the front desk does not, so a new admission is promised a bed that is already occupied.
The evening consultant's verbal order is not on the chart when the night nurse comes on duty.
Dressings, injections and a second scan were done but never reached billing, so the hospital absorbs them.
Pre-authorisation is chased by phone and fax, and the status is known only to one person.
The summary is typed on the day of discharge from a file, delaying the patient and missing details.
Admission raised from OP, casualty or direct; deposit and payer recorded.
A free bed in the right ward is assigned and occupancy updates live.
Consultant orders drugs, investigations and diet on the record during rounds.
Vitals, medication administration and nursing notes charted per shift.
Pharmacy, lab, OT and ward charges accrue; interim bills on demand.
TPA pre-authorisation and claim documents prepared from the record.
Summary generated, final bill settled, bed released.
Workflow: Admitted with a package and a deposit, bed allocated, OT slot booked against the admission, consumables and implants charged as used.
Result: The package bill and the extras are visible before discharge.
Workflow: The evening orders are on the record; the night nurse charts vitals and medication against them.
Result: Nothing depends on a verbal handover.
Workflow: The ward prints an interim statement showing room, pharmacy, lab and procedures to date.
Result: No surprise at discharge.
Workflow: Pre-authorisation raised at admission, enhancement requested as the stay extends, claim documents pulled from the same record.
Result: The claim matches the treatment.
Several wards, ICU and OT on one bed board.
IP-led facilities with a small team.
Short stays with packages and OT charges.
Charts and orders per shift.
Pre-auth and claims from the record.
Yes. An admission can be raised from an OP consultation, from the casualty triage board or directly at the front desk. In each case it continues on the same UHID, so history, orders and previous bills are already attached.
When a bed is allocated at admission, transferred or released at discharge, the ward and bed occupancy view updates for everyone, so the front desk and the ward see the same free beds. See bed management software.
Yes. The IP bill runs as charges accrue from pharmacy, laboratory, OT and the ward, and an interim statement can be printed at any point for the family or the TPA.
Pre-authorisation is raised against the admission with the payer recorded, and claim documents are prepared from the treatment record at discharge. See TPA and insurance billing software.
It is generated from what the record already holds: diagnosis, procedures, investigations, medication and follow-up advice. The consultant reviews and signs it rather than typing it from a file.
Yes. ICU beds with live vitals per bed and operation theatre scheduling are both linked to the admission, so their charges and notes land on the same IP record.
Front desk to discharge.
Live ward occupancy.
Pre-auth and claims.
OT schedule and billing.
Live vitals per bed.
Which one you need.
One record across departments.
Planned stays billed as packages.
Tell us how you work today. We will show you what the platform would look like for you, and give you a clear scope and timeline.
Founder-led · Chennai, India · Built and supported by the person who wrote it